Pain is one of one of the most usual factors people call an ambulance. In the rear of a moving automobile, with equipment rattling and no warranty of a fast health center handover, the standard you set in those first mins shapes the client's trajectory. The device PUAEME008 Supply Pain Management equips -responders to evaluate, deal with, and re‑assess discomfort securely in the pre-hospital context. It mixes scientific judgment with functional self-control. The end results are concrete: fewer call for help on scene, smoother extrication, much safer transport, and boosted individual fulfillment. For many clinicians, it additionally serves as a foundation enter more comprehensive discomfort monitoring courses and certification pathways that branch out practice beyond emergency situation care.
This overview unloads the abilities, evaluations, and end results that PUAEME008 anticipates. It links those expectations to everyday job, and it points to sensible training routes, whether you are a paramedic in a rural station, a registered nurse moving into event medication, or a physio therapist seeking proficiency in emergency pain administration for sports coverage. The emphasis stays on what actually works when time is short and the image is messy.
What PUAEME008 Covers and Why It Endures
The device sits within public security and emergency situation management training bundles in Australia. Its range is deliberately useful: safe, timely, and moral administration of discomfort alleviation in the area. Grads ought to be able to assess pain, select the ideal method, administer within scope, display effect, and escalate when needed. The unit supports service providers that might deal with a kid with a broken forearm at a sports oval, a farmer with a crush injury in a shed, or an older adult with a hip crack on a cool washroom floor.
It is not a pharmacology lecture disguised as a competency. You will certainly find out analgesic alternatives relevant to your scope, however you invest as much time on individual analysis and atmosphere control as on application charts. The greatest practitioners become nimble at gathering the minimal information required to act without missing warnings. They keep protocols at their fingertips, yet they tailor to the individual in front of them.
PUAEME008 also functions as a bridge. Numerous who complete it later go after a discomfort monitoring certificate course or pain management qualification that broadens to chronic and procedural discomfort. Others stitch it right into a mosaic of short training courses in pain management and progressed life assistance, producing a profile that fits event health, extracting sites, or retrieval solutions. Since the unit straightens with a slim but critical piece of care, it maintains its value throughout settings.
Assessing Discomfort When Time and Room Are Tight
The evaluation sequence is greater than a range. It is an organized discussion, visual check, and fast physical examination that records both the extent and the pattern.
You begin with the client's words. Ask open, after that concentrated questions: Where is the discomfort, what does it feel like, when did it start, what makes it worse or far better? If you are using a mathematical ranking scale, established context. I will certainly ask you to rate your discomfort from no to ten, where zero is no pain and 10 is the worst you can picture. Also experienced clinicians miss this sentence, and clients react with a number that does not certificate course in pain management match their internal yardstick. In children, use encounters ranges or straightforward descriptors. In nonverbal grownups, sew with each other taking a breath pattern, articulation, face tension, muscular tissue protecting, and vital indicator trend.
You correlate the story with visuals and palpation when appropriate. Look for asymmetry, deformity, strained compartments, pallor, cyanosis, and swelling that breakthroughs throughout your time on scene. Relocate joints proximally and distally only if it does not get worse injury. Take into consideration a second survey when the system suggests covert injuries. I as soon as treated a person who infatuated on surface forearm pain after an autumn, only for a fast hips rock and leg-length check to reveal an extra severe hip injury. The discomfort they report is not constantly the pain that will certainly eliminate them.
Vital signs matter, however they can misdirect. High blood pressure and tachycardia can reflect discomfort, fear, or hypoxia. On the other hand, a well-conditioned professional athlete might show marginal modification in spite of severe discomfort. Educated pattern recognition helps: a groaning patient with a rigid abdomen and a heart rate increasing from 90 to 110 commonly needs fast transport and mindful analgesia, not expanded probing.
Consciousness and cognition become part of the assessment. A head-injured individual who can not track a basic conversation can not dependably self-report. Adjust your assessment strategy and hire a caretaker, however avoid letting third parties overwrite the person's own assumption if the client has the ability to communicate.
Pharmacological Alternatives Within Scope
The device recognizes that extents differ. A fundamental responder may have dental or inhaled alternatives; advanced companies might bring IV or IO representatives. The task is not to remember every medicine on the market, however to understand secure use of those you carry.
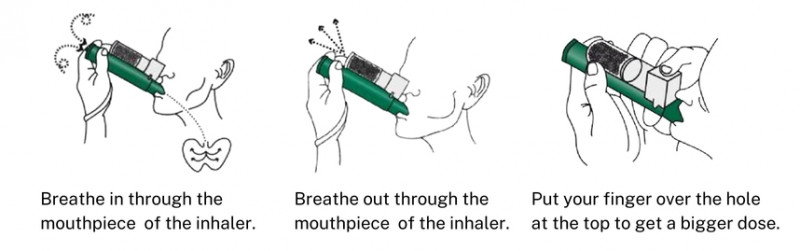
- Methoxyflurane: A staple in several pre-hospital kits for modest to serious discomfort, especially musculoskeletal injuries. Fast onset, non-invasive, and patient-controlled breathing. Secret training factors include protecting against overexposure throughout prolonged usage, making certain adequate air flow in restricted rooms, and staying clear of use where deadly hyperthermia risk or considerable kidney disability is presumed. For anxious people, the act of holding the inhaler adds a sense of control that frequently alleviates the general distress curve. Oral analgesics: Paracetamol and NSAIDs stay workhorses for light to modest discomfort if the person can ingest and has no contraindications. Splinting plus dental analgesia can reduce transportation pain for straightforward fractures. Watch for timing, advancing dosage with individual's self-medication, and NSAID warns in kidney condition, peptic abscess, and bleeding risk. Nitrous oxide/oxygen mix: Useful for step-by-step pain like control or extrication. It requires devices checks, proper scavenging, and focus to people with pneumothorax or bowel blockage where gas development presents risks. The brief half-life allows quick review after the procedure. Opioids: Morphine and fentanyl prevail at sophisticated levels. They remain reliable for serious discomfort when titrated to effect, especially in injury. The pre-hospital context elevates the relevance of respiratory tract watchfulness, advancing sedation with alcohol or benzodiazepines, and incremental dosing with clear endpoints. Fentanyl's hemodynamic security commonly makes it a recommended choice in hypotensive trauma. In older grownups, begin with smaller increments and extend your reassessment periods a touch longer. Ketamine: In advanced methods, low-dose ketamine uses strong analgesia with very little breathing depression. It radiates in hypovolemia, burns, and trapped clients. Development phenomena are uncommon at analgesic doses yet can be mitigated with quiet mentoring and, if range permits, a small benzodiazepine accessory. Stay clear of the lure to rush the dose; a slow push over a number of mins smooths the ride.
The heart of PUAEME008 is safety. Whatever agent you choose, validate five legal rights, check for allergies and considerable comorbidities, record set numbers where required, and display oxygenation, air flow, perfusion, and mental status. Never let a syringe secure your attention greater than the individual's upper body surge and fall.
Non-Pharmacological Measures That Outperform Their Reputation
A surprising quantity of discomfort yields to basic steps that call for no prescription. Rigid splinting for long-bone fractures, sling and swathe for shoulder injuries, mild grip and alignment within extent, and padding bony importances all matter. With burns, early cooling with awesome, not chilly, water for up to twenty minutes boosts discomfort and end results, but do not delay transport for extended air conditioning on deep or extensive burns.
Positioning stays an effective device. Patients with stomach pain often like knees flexed. Upper body pain clients generally select a semi-Fowler position that alleviates lack of breath. Respect their chosen posture unless it disputes with other priorities like spinal protection.
Psychological assistance changes physiology. Talk in constant tones, established assumptions, and tell your actions. On a country road after a rollover, I invested two minutes describing specifically what the splint would seem like as I used it. The individual's respiratory system rate alleviated from 28 to 20 before we touched the arm or leg. PUAEME008 treats such interaction as an expertise, not a soft add-on.
Cold and warm therapies rely on the injury. Ice reduces swelling and discomfort in acute strains and pressures, ideally wrapped to prevent skin injury. Heat can aid muscle mass convulsion, however prevent it in intense trauma or where swelling is developing.
Special Populations, Refined Differences
Children interpret pain with household signs and atmosphere. A parent's face will matter more than your uniform. Get down to eye level, show the mask or inhaler initially, and allow them touch non-threatening tools. Dosage drugs on weight, not age, and validate numbers with caregivers and your referral. Step-by-step pain rises steeply in children, so strategy analgesia prior to cannulation or crack adjustment. Take into consideration that dehydration accelerates medicine impacts and side effects. Reassess typically and record behavior, not simply numbers.
Older adults present a various difficulty. They might under-report discomfort or normalize it. Polypharmacy and comorbidities increase risk. Review for ecstasy and cognitive disability. Avoid opioid stacking with existing sedatives, and titrate gradually. For hip cracks, gentle positioning and grip, plus a warm pack to the lumbar region for muscle relaxation, can save an opioid dose or 2. In the existence of renal condition, be judicious with NSAIDs.
Pregnancy complicates pharmacology and positioning. Side tilt beyond mid-second trimester secures venous return. Several solutions like fentanyl or low-dose morphine over NSAIDs in late pregnancy. Abdominal discomfort in pregnancy deserves a reduced limit for transportation and consultation.
Patients with material usage disorders should have the very same roughness as anybody. Prevent stigmatizing language. Titrate to result, record objectively, and maintain safety via positioning and surveillance. Blended intoxication with alcohol can mask hypoventilation, so establish a high bar for pulse oximetry and capnography where available.
Scene Management and Crew Coordination
Emergency pain administration does not occur in a vacuum. The unit expects you to incorporate analgesia with scene safety and security and logistics. If extrication is pending, prepare your analgesic window so pain relief comes to a head during motion. On a high driveway with a breakable shoulder dislocation, we adjusted timing so methoxyflurane gotten to result right as the individual transitioned to the inside story stretcher.
Agree on duties. One medical professional handles the respiratory tract and monitors sedation degree. The other interacts dosing out loud and papers. Closed-loop communication prevents double application, especially when syringe swaps occur under tension. Alert receiving facilities to medicines offered, timing, and impact so they can build on your strategy as opposed to repeat or reverse it.
Equipment checks are not busywork. A missing mouthpiece, an empty nitrous cyndrical tube, or a dead suction battery can hinder great purposes. Several teams use brief responsive checks at shift beginning: turn the valve, really feel the flow, click the capnography wire, press the bag. Discomfort management training programs typically construct these routines into simulation situations to make them automatic.
Documentation that Informs the Story
A crisp narrative supports client security and legal defense. Chart initial pain descriptors, scale rating, and location. Compose what you offered, just how much, when, and why you chose it. Include non-pharmacological steps, person placing, and splinting method. Reviews need to check out like a timeline: 14:12 fentanyl 25 mcg IV, 14:16 discomfort 8 to 6, RR 18, SpO2 98 percent on 2 L. Withstand need to document only numbers. Behavior, face, and feature supply richer detail. Patient able to bear weight with assistance at 14:29 brings more meaning than an only score.
When discomfort stays refractory, note what you dismissed and your rise actions. If you spoke with clinical control or senior clinicians, detail their assistance. In multi-agency occasions, share a summary with on-scene managers to prevent therapy gaps.
Training Pathways: From System Competency to Certification
Many companies begin with PUAEME008 as a targeted tipping rock. It provides a practical toolkit you can utilize the following change. From there, individuals diverge based on function and interest.
- Pain management training for nurses: Nurses in immediate treatment, perioperative setups, or remote centers typically add advanced assessment, step-by-step analgesia, and titration procedures. Pain management programs for registered nurses occasionally include modules on multimodal therapy and opioid stewardship customized to nursing extent. Certificate programs might pile PUAEME008 with injury treatment, IV treatment, and sedation competencies. Pain monitoring programs for physio therapists: Physios that cover sporting activities events or work alongside emergency teams gain from sharp pain frameworks, splinting, and non-pharmacological methods. These pain management training courses value the physical rehabilitation extent while instructing clear referral triggers. Combination with trauma and back assessment components is common. Provide pain monitoring course for pre-hospital practitioners: Rescue services and occasion medication carriers run short programs in pain administration, typically straightened to PUAEME008 offer discomfort monitoring. They focus on breathed in agents, nitrous, and opioid titration with extensive air passage surveillance. The better programs include nighttime and cramped-space simulations. Pain administration certificate and accreditation paths: If you intend to expand past intense treatment, look for a certification course suffering monitoring that deals with severe, chronic, and cancer cells discomfort. A pain administration accreditation program normally covers neurobiology, psychology of pain, useful assessment, and pharmacology across the continuum, plus interaction skills and honest considerations. Some programs recognize prior picking up from PUAEME008 and shorten your path.
Not all discomfort administration training courses are equal. Assess course hours, professors experience, simulation realistic look, and post-course assistance. Ask whether situations mirror your practice setting. I favor programs that consist of failed-response scenarios and gray-zone choices, not simply textbook fractures.
The Skill of Titration and the Art of Timing
Titration separates positive carriers from hesitant ones. The objective is not lack of pain, however appropriate pain that preserves safety and function. For several injury people, moving from a 9 to a 4 or 5 allows you splint and transportation without fogging the airway. That equilibrium takes dosages in tiny actions and stops briefly for effect. Fentanyl comes to a head fast, ketamine a little bit slower at analgesic dosages, and dental agents delay by 10s of mins. Your strategy must respect these pharmacokinetics.
Timing issues as much as the total dose. If you will lug a person down 3 flights, peak impact must reach the touchdown, not at the visual. For step-by-step actions like shoulder decrease, pick either rapid titration of a short-acting agent or a ketamine analgesic dose with quiet mentoring, depending on scope and ability mix.
Beware dose momentum. After two little dosages generate only tiny gains, groups commonly jump to a huge third dose that overshoots. Perseverance and reassessment protect against see-sawing in between discomfort and oversedation. Usage capnography where possible. A refined upward creep in ETCO2 might be your initial warning.
Ethical Grounding: Approval, Equity, and Opioid Stewardship
PUAEME008 anticipates you to obtain grant the degree possible, even under stress. Discuss benefits and risks in plain language. A straightforward manuscript jobs: I can offer you a medicine through your capillary that need to decrease your discomfort in a couple of minutes. It can make you sleepy and slow your breathing a little bit, so I will enjoy you very closely. Is that all right? For breathed in agents, demonstrate and let the individual hold the tool when appropriate.
Equity issues. Individuals from marginalized groups typically report receiving much less analgesia for the very same injuries. Develop a practice of structured evaluation and documentation to counter implicit prejudice. If your numbers and story warrant therapy, follow through irrespective of accent, age, or regarded stoicism.
Opioid stewardship in the pre-hospital area rests on titration, monitoring, and handover clearness, not on withholding needed analgesia. Your duty is to eliminate acute suffering safely, not to establish long-term opioid trajectories. Clear documents and communication support the getting team in intending following actions, including non-opioid techniques and discouraging when appropriate.
Measuring End results That Matter
The simplest marker is the discomfort score pattern prior to and after treatment, however end results exceed a number. Watch for improved resistance of needed motion, reduced stress and anxiety, secure vitals, and emergency pain management techniques the absence of negative occasions. In service audits, meaningful outcomes consist of the portion of eligible injury people who obtained timely analgesia, median time to initial dose, and the rate of considerable respiratory anxiety per 1,000 managements. Several solutions also track patient-reported experience measures at follow-up. Comments like They told me what to anticipate and I really felt took care of commonly associate with far better physiological trajectories.
For private professionals, keep an individual log. Note what worked, what didn't, and why. Patterns emerge: dosing that is consistently slow-moving, skills that need refresher courses, or protocols that can use explanation. Bring these observations to training leads. Great discomfort administration training adapts based on frontline feedback.

Common Pitfalls and Practical Fixes
Two errors recur. The initial is dealing with the number, not the individual. A young adult who ranks discomfort at 10 yet laughs with buddies may be using the range differently or dealing well. Concentrate on function and behavior also. Can they move with assistance, or do they stiffen and guard at every motion?
The secondly is avoiding the second look. After the initial wave of analgesia, re-examine the hurt location et cetera of the body. Swelling may have advanced. A limited splint may require helping to loosen. That five-minute check prevents issues and adjusts dosing.
Other side instances should have attention. In thermal burns, avoid heavy dosages that shadow air passage evaluation. For abdominal discomfort where surgical treatment is likely, contemporary proof supports proper analgesia as opposed to the old concern of covering up indicators. Still, keep doctors in mind and file searchings for plainly prior to and after treatment. In presumed area disorder, discomfort out of proportion and discomfort on passive stretch persist despite analgesia. Escalate early.
Building Skills With Calculated Practice
Competency climbs with repetition, but random repetition is sluggish. Deliberate practice presses learning time. Create micro-drills. Before each change, verbalize your methoxyflurane contraindications while you establish the set. When you restock fentanyl, rehearse a three-step titration plan for a 70 kg adult and a 40 kg older adult. Pair with a colleague and review each various other's authorization scripts.
Simulation must seem like work. Dim the lights, add noise, and mimic the ache in your shoulder as you kneel by a car seat. Run series where the client does not react to your first strategy so you practice escalation without panic. Make use of a metronome for slow-moving ketamine pushes to avoid the too-fast hand that invites side effects.
Finally, invest in wider learning. A discomfort monitoring certificate or a structured discomfort administration program exposes you to the biopsychosocial design and multimodal strategies. Physio therapists will certainly deepen non-pharmacological tactics. Nurses will improve titration in step-by-step settings. Pre-hospital service providers will harmonize sedation ranges with transportation realities. The most effective programs treat PUAEME008 as a support point and build external with nuance.
The Payback: Calmer Scenes, More Secure Transports, Better Trust
The first time you decrease a person's 9 out of 10 to a workable 4 as you fill them, you feel the area change. Households take a breath. Team members quit watching the clock and start believing two moves ahead. The person keeps in mind that ride in different ways, and they are more probable to involve with treatment on arrival. Throughout thousands of instances, this translates right into fewer combative transportations, less fell short treatments, and less negative events.
PUAEME008 Offer Discomfort Administration educates not only just how to push a medicine or use a splint, but exactly how to orchestrate the little choices that make severe pain bearable without endangering security. It prepares you for the cramped rooms and imperfect info that specify pre-hospital job. Match it with proceeded discomfort management training, look for comments, and keep refining. The ability deserves the initiative, and the end results reveal on every shift.